Ipamorelin research: peptideresearchalliance
A convincing growth-hormone pulse and an unsuccessful clinical test belong in the same account. Each asks a different question of ipamorelin; neither earns authority over the other.
The human bowel-surgery study
Ipamorelin’s published Phase 2 trial tested recovery after bowel resection. Postoperative ileus is the sluggish return of bowel function after surgery; a ghrelin-receptor agonist offered a plausible way to help the gut move again.
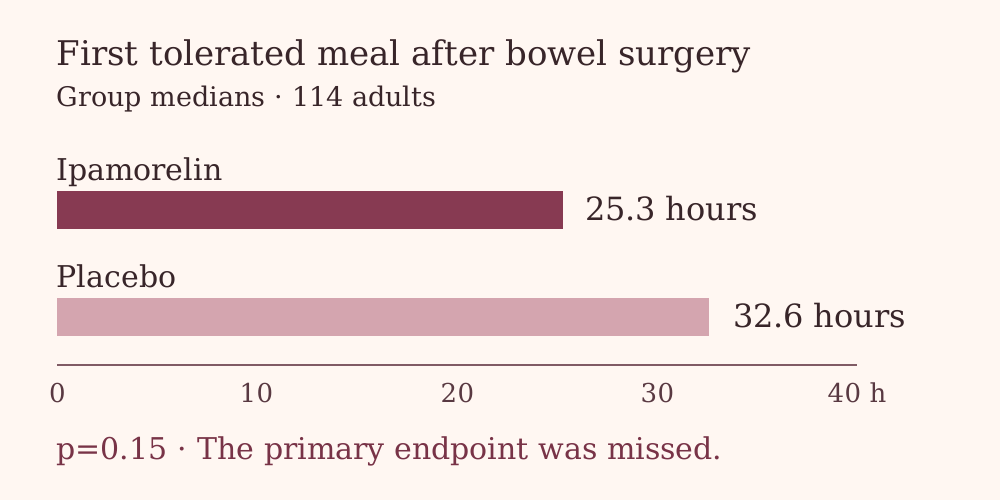
The 2014 randomized trial in 114 adults reported median time to first tolerated meal of 25.3 hours with ipamorelin and 32.6 hours with placebo, with p=0.15. The primary endpoint was missed. No ipamorelin-specific safety signal was identified during that short perioperative observation.
I count a useful disappointment here. There is a numerical difference, and there is the trial’s failure to demonstrate efficacy on its chosen primary outcome. Enthusiasm about growth hormone cannot repair that result. Equally, a failed bowel-recovery endpoint says little about every other conceivable effect of the molecule.
Ipamorelin mechanism of action
Ipamorelin is a synthetic pentapeptide that activates the ghrelin receptor, GHS-R1a. In the pituitary, that receptor can trigger release of growth hormone. Its reputation for selective GH release comes from preclinical pharmacology; the familiar cortisol, ACTH and prolactin comparisons need that animal-study context.
For the human response, the 1999 pharmacokinetic and pharmacodynamic study is a more precise starting point. Healthy male volunteers showed a single GH pulse peaking at about 40 minutes after intravenous administration. Terminal half-life was approximately 2 hours. This establishes a hormone response under the study’s conditions, leaving the promised changes in sleep, appearance and athletic recovery to be tested separately.
When a search asks for an “ipamorelin cortisol prolactin human study,” I’d ask which part of that combined question was actually tested in humans. The human dataset here characterizes ipamorelin concentrations and a GH response; the celebrated selectivity comparisons arose chiefly in animals. A claim about fewer hormonal effects needs its own evidence beyond a picture of one rising hormone.
The human pulse interests me. The long list of benefits often attached to it asks considerably more of that small experiment.
Bone; ferrets
The rat bone-growth study found faster longitudinal bone growth in adult female rats, with no measurable change in systemic IGF-1, IGF-binding proteins or bone-turnover markers. The absent change in circulating IGF-1 makes that a particularly awkward result for a simple hormone story: a skeletal measurement changed while the expected circulating marker stayed steady.
A later ferret experiment addressed weight loss caused by cisplatin. Ipamorelin reduced that weight loss, yet did not reduce vomiting in the model.
Neither animal study establishes human fat loss, muscle gain or relief from chemotherapy symptoms. Their value is in the particular responses they revealed and the next experiments those responses suggest.
Ipamorelin safety
Reduced cortisol or prolactin spillover would be a useful selectivity feature, but chronic safety is a much larger question. The human bowel-surgery trial and acute hormone-response study offer short observations. They cannot establish a long-term safety profile.
There is a relevant neighboring warning. A study of GSK894281, a different ghrelin-receptor agonist, found myocardial degeneration and necrosis in rats after 28 days. Ipamorelin was not the tested compound. I’d ask harder questions about the receptor class after that neighboring injury, with care to avoid attributing another compound’s injury directly to ipamorelin.
Sleep improvement, vivid dreams, recovery, puffiness, appetite changes and flushing appear in community accounts. These are anecdotal accounts, not clinical evidence, and the product identity and accompanying circumstances are uncertain. They do not establish efficacy for anti-aging, body composition or sleep.
Regulatory position
Ipamorelin has never received drug approval. On FDA’s page current as of April 22, 2026, ipamorelin acetate has a withdrawn 503A nomination with safety concerns retained, and remains in Category 2 for 503B outsourcing facilities. Withdrawal alone does not establish permission for patient-specific compounding. WADA prohibits growth-hormone secretagogues, including ipamorelin, at all times under S2.
The missed clinical endpoint is therefore central to its history, rather than an inconvenient footnote to a story of delayed approval. The comparison with the other compounds gives that history some useful company.